Repeated right-upper-abdominal pain is more important than the mere presence of gallstones when deciding whether to seek surgical advice. By matching your symptoms with ultrasound and blood-test findings, you can distinguish stones that need observation from disease that needs prompt gallbladder removal or bile-duct treatment.
Key takeaways
- Seek urgent care for severe pain with fever, jaundice, persistent vomiting or abdominal tenderness.
- Ultrasound shows stones; blood tests identify inflammation, bile duct blockage or pancreatitis.
- Repeated biliary colic usually warrants a planned surgical consultation after the first attack.
- Non-surgical treatments may leave the gallbladder and future attacks in place.
Which gallstone symptoms justify a surgical consultation or urgent assessment?
Steady right-upper-abdominal pain or upper-middle abdominal pain lasting at least 30 minutes and sometimes several hours justifies a surgical consultation, especially when it follows pain after fatty meals. These biliary colic symptoms often include nausea or vomiting; repeated attacks make planned treatment worth discussing.
Gallstone symptoms such as indigestion, bloating, burping, or vague discomfort alone are less reliable evidence. Gallstones may be present without causing those sensations, and surgery may not remove symptoms caused by reflux, ulcers, irritable bowel syndrome, or another condition.
| Pattern | What it suggests | What to do |
|---|---|---|
| First short attack without fever or jaundice | Possible uncomplicated biliary colic | Arrange planned medical and surgical evaluation |
| Repeated typical attacks | Recurrent biliary colic | Discuss elective laparoscopic cholecystectomy |
| Pain lasting several hours with fever | Possible acute cholecystitis | Seek same-day hospital assessment |
| Pain with jaundice, dark urine, or pale stools | Possible bile-duct obstruction | Seek urgent hospital assessment |
Go to hospital rather than waiting for a routine appointment if you have:
- Persistent or severe abdominal pain
- Fever with chills
- Yellow skin or eyes
- Dark urine or pale stools
- Confusion
- Repeated vomiting that prevents drinking
A first short attack can lead to planned ultrasound and blood-test evaluation. Prolonged pain with fever or jaundice needs faster treatment because infection or a blocked bile duct can worsen quickly. Loss of appetite or nausea without characteristic pain is less specific and still deserves assessment if it persists.
What do ultrasound and blood tests reveal about the need for treatment?
Ultrasound findings guide treatment; they do not make surgery automatic. Gallstones on ultrasound in someone without pain or complications are often observed, because an incidental stone is not itself a reason for cholecystectomy.
When symptoms and examination suggest acute cholecystitis, clinicians look for a matching pattern:
- Gallbladder-wall thickening, which supports inflammation when it accompanies right-upper-abdominal tenderness and persistent pain.
- Fluid around the gallbladder, which adds evidence of local inflammation.
- A distended gallbladder, which can indicate obstruction at the gallbladder outlet.
A widened common bile duct raises concern that a stone has moved beyond the gallbladder. A normal ultrasound does not exclude a small duct stone because it may not be visible.
Liver-function tests help assess obstruction. Ask whether bilirubin, alkaline phosphatase and aminotransferases are normal or rising; the results are interpreted alongside symptoms and the scan, not in isolation.
When the risk of a common-bile-duct stone is intermediate, magnetic resonance cholangiopancreatography (MRCP) or endoscopic ultrasound can provide a closer view without proceeding directly to an invasive treatment. ERCP is considered when a common bile duct stone, cholangitis or another urgent duct problem is suspected or confirmed.
It is not a routine diagnostic scan, and it does not remove stones remaining inside the gallbladder.
When is laparoscopic cholecystectomy recommended after a first attack or complication?
The decision after a first gallstone attack depends on whether the stones are incidental, causing typical pain, or producing a complication. Use this sequence:
1. Asymptomatic gallstones found by chance usually need observation, not cholecystectomy. Consider removal when a high-risk condition or a specific complication risk changes the balance.
2. A first brief episode of typical biliary pain usually leads to a surgical consultation and planned follow-up, not automatic emergency surgery.
Recurrent steady pain in the right upper abdomen or upper middle abdomen, especially after meals and lasting at least 30 minutes, is a usual reason to offer elective laparoscopic removal because another attack is difficult to predict.
3. Acute calculous cholecystitis usually favours acute cholecystitis surgery during the same hospital admission. Aim for laparoscopic removal within one week of diagnosis, commonly within 72 hours when feasible, rather than routinely waiting several weeks.
4. After mild gallstone pancreatitis, remove the gallbladder before discharge once you are stable. Severe pancreatitis with necrosis or ongoing systemic complications can require delaying surgery until the inflammation and organ problems settle.
5. Frailty, sepsis, major heart or lung disease, coagulopathy, or inability to tolerate general anaesthesia can make immediate surgery unsafe. Doctors may begin antibiotics and perform percutaneous cholecystostomy to drain the gallbladder, then reconsider surgery after fitness improves.
6. A stone in the common bile duct requires duct clearance as well as a plan for gallbladder removal. ERCP or another duct procedure may come before or around laparoscopic cholecystectomy.
What are the practical alternatives, and what can each one fail to solve?
Observation fits symptom-free gallstones, not repeated typical attacks or complications. Each option solves a different problem, and each leaves something unresolved:
| Option | What it can solve | What it can fail to solve |
|---|---|---|
| Observation | Avoids an operation when stones cause no symptoms | Does not prevent another attack or treat inflammation, pancreatitis or obstruction |
| Diet and medicines | Smaller meals and avoiding foods that trigger pain may reduce symptoms | Diet and gallstones: diet does not dissolve established stones or reliably prevent attacks; medication is not a dependable replacement |
| ERCP | Clears a common bile duct stone lodged outside the gallbladder | ERCP for bile-duct stones does not remove the gallbladder, the source of future stones, so it is not usually a substitute for cholecystectomy |
| Laparoscopic cholecystectomy | Removes the gallbladder and prevents gallbladder attacks from its stones | It does not extract a stone already lodged in the common bile duct |
| Open cholecystectomy | Provides safer access when keyhole surgery cannot maintain safe anatomy | Recovery is usually more demanding than after laparoscopic surgery |
A common bile duct stone needs duct clearance, usually by ERCP or selected surgical exploration, plus treatment of the gallbladder when appropriate. Open cholecystectomy may be safer with severe inflammation, scarring, bleeding, unclear anatomy or a condition that makes laparoscopic surgery unsuitable.
Pregnancy does not automatically exclude laparoscopic cholecystectomy. Disease severity, trimester, anaesthesia assessment and obstetric input guide the choice when symptoms cannot be controlled without surgery.
How should you weigh surgical safety before choosing gallbladder removal?
Safety depends on more than the size of the incisions. A gallbladder surgery consultation should review:
- The number and duration of attacks, jaundice, pancreatitis, fever and vomiting
- Medicines, especially blood thinners, diabetes drugs and steroids
- Pregnancy or plans for pregnancy
- Previous abdominal surgery, heart disease and lung disease
- Ultrasound findings, liver blood tests and the risk of a common bile duct stone
Discuss laparoscopic cholecystectomy risks plainly: bleeding, infection, bile leak, a retained duct stone, injury to the intestine or other nearby organs, and bile-duct injury. A duct injury is uncommon but can require ERCP, repeat surgery or reconstruction.
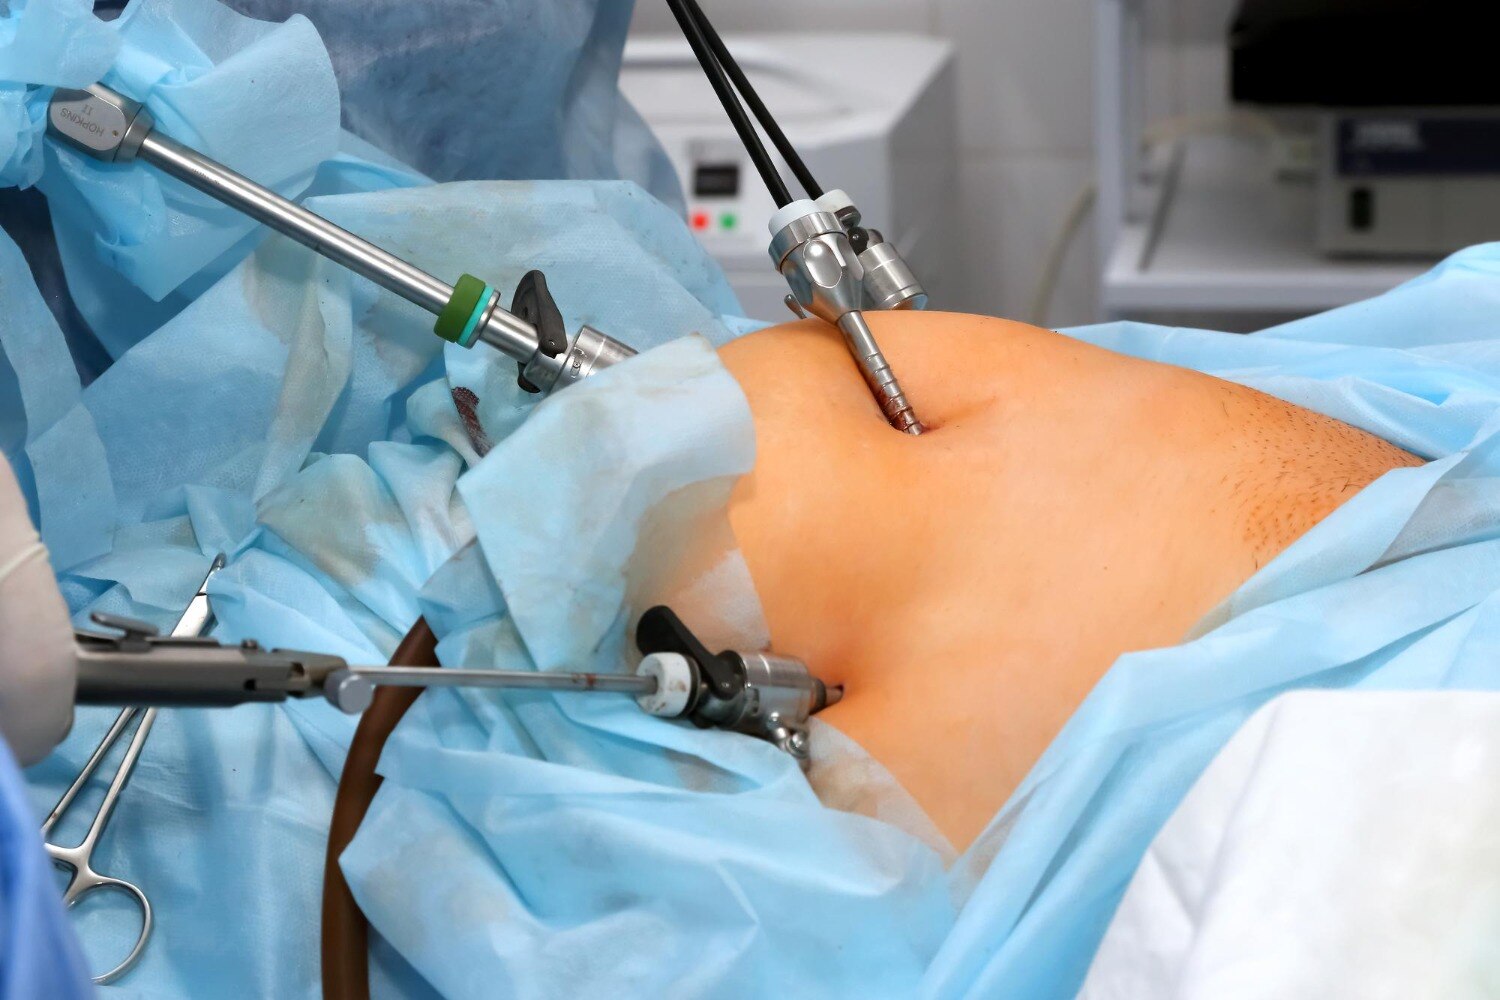
During surgery, the critical view of safety means identifying the cystic duct and cystic artery, then confirming that only those two structures enter the gallbladder before either is divided. If inflammation, scarring or distorted anatomy prevents that view, subtotal cholecystectomy or conversion to open surgery can be safer than continuing.
| Finding | What it may mean | Possible plan |
|---|---|---|
| No symptoms and low-risk tests | Stones are incidental | Observation |
| Typical attacks with safe anatomy | Symptoms are likely gallstone-related | Planned surgery |
| Jaundice or a widened duct | A duct stone needs consideration | MRCP, endoscopic ultrasound or ERCP |
| Severe inflammation or unclear anatomy | Standard dissection is unsafe | Subtotal surgery or conversion to open surgery |
After removal, bile still flows from the liver into the intestine. Temporary loose stools or urgency can occur; persistent symptoms need reassessment for another diagnosis. Dr. Shaunak Saha in Baner, Pune, can help review whether observation, urgent treatment or planned surgery fits your scan, blood tests and duct-stone risk.
Related service
Laparoscopic General Surgery Laparoscopic cholecystectomy is a minimally invasive surgical procedure used to remove the gallbladder, most commonly when gallstones cause recurrent... View service → |
Frequently asked questions
Which gallstone symptoms require urgent assessment?
Seek urgent assessment for severe or persistent upper-abdominal pain with fever, jaundice, repeated vomiting, marked tenderness, confusion or fainting. These symptoms can indicate cholecystitis, bile duct obstruction, cholangitis or pancreatitis.
What do ultrasound and blood tests reveal about gallstones?
Ultrasound can show gallstones, gallbladder-wall thickening, fluid around the gallbladder and bile duct widening. Blood tests including a complete blood count, bilirubin, alkaline phosphatase, ALT, AST and lipase help identify infection, obstruction or pancreatitis.
When is laparoscopic cholecystectomy recommended?
Surgeons commonly recommend laparoscopic cholecystectomy for repeated biliary colic, acute cholecystitis, gallstone pancreatitis after stabilisation, or stones in the common bile duct after that duct is cleared. Timing depends on the complication and your surgical risk.
What alternatives exist to gallbladder removal?
Observation suits people with incidentally found stones that cause no symptoms. Pain medicines and dietary changes do not remove stones. ERCP can clear common bile duct stones but leaves the gallbladder behind, while drainage procedures suit selected high-risk patients and do not provide the same definitive treatment as removal.